BPC-157 and TB-500 compared
A shared interest in repair conceals different molecules, different experiments and very different human records.
Sequence
The comparison in context
I would compare these compounds by the experiments they can support before comparing their reputations. The BPC-157 review describes a broad animal literature with three small human pilots. The thymosin beta-4 review concerns the full protein behind much of TB-500’s repair reputation.
Molecules and models
| Subject | Identity | Main evidence discussed here |
|---|---|---|
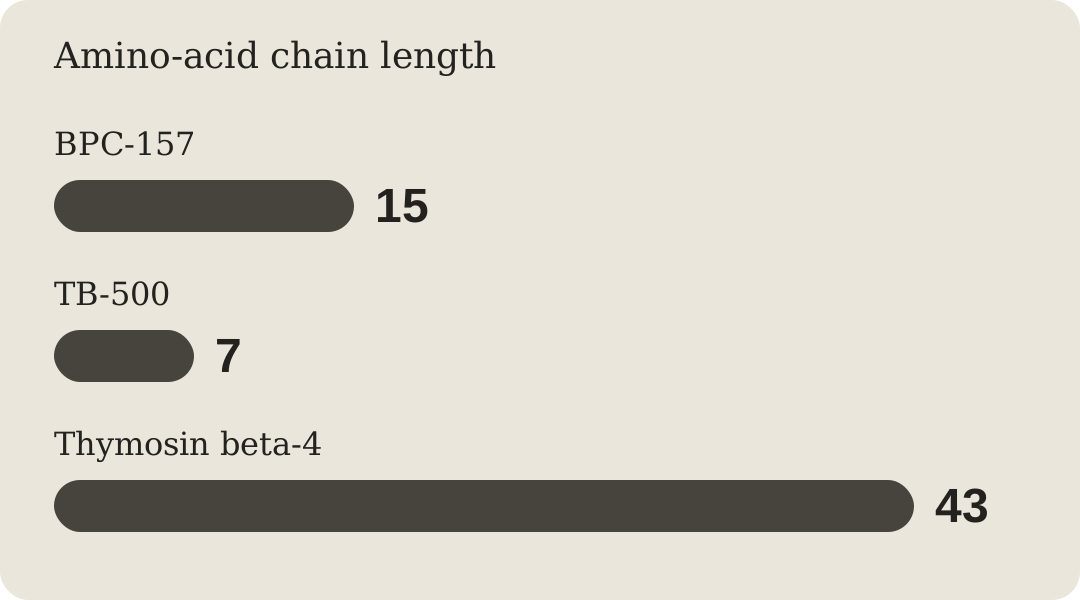
| BPC-157 | Synthetic gastric peptide, 15 amino acids | Rat healing models; cell mechanisms; three small human pilots |
| TB-500 | Synthetic Ac-LKKTETQ fragment, 7 amino acids | Actin-binding motif; controlled human safety and efficacy unestablished |
| Thymosin beta-4 | Full parent protein, 43 amino acids | Animal wound and cardiac studies; Phase 1 human safety study |
The BPC-157 review and thymosin beta-4 review supply the context for these identities. Chain length is a physical difference, with no automatic ranking of potency or clinical usefulness.
Cell mechanisms
BPC-157’s VEGFR2 experiment connected vessel growth with receptor expression and internalization in cultured cells and animal models. Full-length thymosin beta-4’s actin structure explains sequestration of free actin units, part of the biology behind cell movement.
Both research stories involve angiogenesis. That overlap makes a biological connection plausible, although a common downstream process tells us little about the benefit of combining them. Direct controlled human combination research would have to settle that question for me.
The human samples
The BPC-157 intravenous pilot involved two healthy adults and reported no adverse events or measurable changes in its safety biomarkers. The full-length thymosin beta-4 trial was randomized and placebo-controlled, involved 40 healthy volunteers, and reported no serious adverse events or dose-limiting toxicities.
The designs and sample sizes differ, and the latter trial concerns full-length thymosin beta-4. Neither result demonstrates human injury-repair efficacy for the TB-500 fragment. I give the controlled trial credit for its design and the full-length protein credit for its own result.
Administration and clearance
BPC-157 studies used intramuscular and intragastric routes in rats with gastric ulcers, with additional routes across its wider literature. The rat-and-dog pharmacokinetic study reported an elimination half-life under 30 minutes and different intramuscular bioavailability in the two species.
Full-length thymosin beta-4 was given intravenously in the human safety trial and topically or intraperitoneally in rat wound work. These are descriptions of experiments. The cited studies establish no human dosing regimen for BPC-157 or TB-500.
Safety questions
For BPC-157, the review raises the heavy reliance on animal work, limited confirmation by other research groups and unregulated availability. For TB-500, extrapolation from the parent protein adds an identity problem. The parent protein’s role in cell migration and vessel growth also creates a theoretical tumour-related concern.
The sports-medicine review places both in a field with scarce rigorous human safety data. I regard unknown long-term safety as a central question rather than a small qualification to a list of benefits.
Regulatory / WADA status
Neither compound is an approved medicine. BPC-157 is prohibited in sport by WADA under the S0 non-approved-substances category [2]. TB-500 is also WADA-prohibited (peptide/growth-factor categories), is a prescription medicine in some jurisdictions such as Australia and New Zealand, and has been encountered as a doping agent in racehorses [6]. FDA’s page, current as of April 22, 2026, lists BPC-157 and TB-500 among “bulk drug substances nominated but withdrawn”; withdrawal is not clearance, approval or permission to compound, and FDA retains its stated safety concerns.
One more line on the map is worth drawing. The BPC-157 and TB-500 studies are this digest’s concern; Promise Peptides (mypromise.com) is a separate licensed U.S. telehealth provider, now prescribing prescription-only peptide care within its catalog. Research-labelled material is still sold, a market distinct from that prescription care.
U.S. prescription limits
That licensed telehealth provider’s care is open only to patients in the United States. Its licensed U.S. clinician weighs the individual case and can decline to prescribe; its options also turn on the patient’s state and the treatment. Any compounded medicine has no FDA approval.
Do the findings support a combination?
The sources on this page do not establish a combined BPC-157 and TB-500 treatment. A vessel-growth result and a full-protein wound result can suggest questions for an experiment; they cannot supply the result of that experiment.
Pairing the compounds adds another claim to test: identified compounds, useful outcomes and follow-up for harms. Until that exists, the most concrete comparison is the one above: separate molecules, separate study conditions and separate unanswered questions.